
Stop Lowball Workers’ Comp Hip Settlements: $66,634 Benchmark & WCMSA

Workers’ compensation claims for hip, thigh, and pelvis injuries averaged $66,634 in claim costs for injuries occurring in 2022 and 2023, according to the National Safety Council’s Injury Facts data. That figure reflects total claim costs, not settlement checks, and your actual number can swing far above or below it depending on whether you had surgery, how your permanent impairment is rated, and whether Medicare set-aside rules apply. Run your numbers through a state-specific calculator before you negotiate anything.
TL;DR:
- Claim costs vary widely depending on injury severity, with surgical hip replacements often exceeding $100,000, while minor strains may be under $20,000.
- Settlement amounts are heavily influenced by permanent impairment ratings, age, occupation, and whether future medical needs like revision surgeries are anticipated.
- Insurers typically settle after maximum medical improvement, but timelines can range from months to over a year, especially when Medicare set-asides are involved.
- Carefully reviewing settlement allocations, Medicare set-aside requirements, and ensuring medical restrictions are well-documented can prevent underfunded future care.
- Using state-specific calculators and preparing your own estimates can strengthen negotiations and help identify lowball offers early.
Table of Contents
- Average Settlement Amounts and What the Statistics Actually Measure
- Valuation Drivers: The Factors That Make a Hip Settlement Higher or Lower
- Types of Hip Injuries That Commonly Show Up in Workers’ Comp Claims
- When Carriers Offer Lump-Sum Settlements and What the Timeline Looks Like
- How to Evaluate a Settlement Offer Before You Sign
- What You Get If You Don’t Settle: TTD, PPD, and Ongoing Medical Coverage
- Do You Need a Lawyer? When Legal Help Changes the Outcome
- State Filing Deadlines and Immediate Steps to Protect Your Claim
- How to Produce a Realistic Estimate Before You Negotiate
- Common Disputes in Hip Workers’ Comp Claims and How to Handle Them
- The Role of Independent Medical Examinations in Settlement Decisions
- How Vocational Rehabilitation and Return-to-Work Programs Affect Settlement Value
- Negotiation Priorities and the Mistakes That Cost Workers the Most
- Get a Personalized Hip Settlement Estimate in Minutes
- FAQ
- Sources
Average Settlement Amounts and What the Statistics Actually Measure
The $66,634 average from Injury Facts covers medical payments and indemnity (wage replacement) combined across all hip, thigh, and pelvis claims, mild and severe alike, for injuries occurring in 2022 and 2023. It is a claim cost average, not a settlement average, and it blends sprains that heal in weeks with hip replacements that require lifetime care. Treat it as a reference point, not a prediction for your own file.

Workers’ comp claims involving the hip, thigh, or pelvis cost an average of $66,634, according to NSC Injury Facts data, a figure that includes both minor strains and catastrophic fractures requiring joint replacement.
Practitioner-reported settlement ranges vary widely because severity drives nearly everything. These figures are illustrative, drawn from the typical spread seen in hip-related claims, not from a single dataset:
- Minor strains or contusions: often $5,000 to $20,000 when the worker returns to full duty without surgery.
- Fractures treated surgically (screws, plates, or rods): commonly $60,000 to $200,000 depending on hardware, recovery time, and any residual limp or stiffness.
- Total or partial hip replacement: frequently higher than fracture cases because of lifetime hardware monitoring, revision surgery risk, and permanent restrictions on bending, lifting, or standing.
- Labral tears treated arthroscopically: usually land between strain and fracture ranges, depending on whether the tear fully resolves.
Averages hide the variables that actually set your number. Two workers with the same diagnosis can land $100,000 apart because one kept working light duty while the other lost a career in physical labor. That is why a generic statistic is a starting point for the conversation, never the final word on your file.
Valuation Drivers: The Factors That Make a Hip Settlement Higher or Lower
Adjusters and attorneys weigh the same handful of variables when they value a hip claim, and understanding them helps you spot a lowball offer before you sign anything.
- Severity, surgery, and permanent impairment rating: a documented surgical procedure and a higher permanent partial disability (PPD) rating generally push value up because they signal lasting loss of function.
- Wage loss, age, and occupation: a younger worker in a physically demanding job faces a longer horizon of reduced earning capacity than an office worker nearing retirement, which changes the indemnity math.
- Preexisting hip conditions: if you had prior arthritis or a prior injury, the insurer may argue for apportionment, reducing the portion attributable to the work injury.
- Future medical costs: ongoing physical therapy, hardware replacement, or an eventual hip replacement all expand the medical allocation in a life care projection.
- Liability strength and litigation risk: when causation is disputed or witnesses are weak, insurers may offer more to avoid a hearing, or less if they believe they would win one.
The Social Security Administration’s policy analysis on permanent partial disability notes that adjudicators weigh age, education, work history, degree of disability, availability of alternative work, and future medical needs when judging whether a settlement is adequate. That is the same checklist worth running against your own offer.
Pro Tip: Ask your treating doctor to put your permanent restrictions in writing before you negotiate: a vague “light duty” note is worth far less than a specific lifting limit or range-of-motion finding.
Types of Hip Injuries That Commonly Show Up in Workers’ Comp Claims
Hip injuries on the job usually trace back to falls from height, slips on wet or uneven surfaces, blunt trauma from equipment or vehicles, or repetitive strain from years of lifting, climbing, or kneeling. The injury type shapes both your treatment path and your settlement ceiling.
- Hip strains and contusions: soft tissue damage from a fall or awkward twist, usually treated with rest, physical therapy, and anti-inflammatories, with full recovery expected.
- Labral tears: cartilage damage around the hip socket, often from repetitive motion or a single traumatic twist, sometimes requiring arthroscopic repair.
- Hip fractures: breaks in the femoral neck or pelvis from falls or crush injuries, typically requiring surgical fixation with screws or plates.
- Hip replacement: total or partial joint replacement, usually reserved for severe fractures, advanced arthritis aggravated by the injury, or failed conservative treatment.
A simple strain rarely produces a large settlement because the expectation is full recovery. A fracture requiring hardware or a replacement that leaves permanent restrictions moves you into a different settlement category entirely, one where future medical needs and permanent impairment ratings dominate the conversation.
When Carriers Offer Lump-Sum Settlements and What the Timeline Looks Like
Insurers typically raise settlement once your condition stabilizes, not before. The most common triggers are:
- Reaching maximum medical improvement (MMI), when your doctor determines your condition has plateaued and assigns a permanent impairment rating.
- Completion of surgery and recovery, once the insurer can see the final medical bill and functional outcome rather than guessing at it.
- Weakening liability or looming litigation costs, when the carrier prefers to settle rather than risk a hearing or pay ongoing defense costs.
Timelines vary widely. A straightforward strain might settle within a few months of MMI, while a hip replacement case with disputed causation or Medicare set-aside requirements can take a year or more. Where federal programs apply, 20 CFR § 702.243 requires a complete settlement application before an adjudicator will approve it, and incomplete submissions delay the process further.
How to Evaluate a Settlement Offer Before You Sign
A settlement offer is a contract, and the details matter more than the headline number.
- Check for explicit allocation between future medical costs and income replacement: vague lump-sum language without a breakdown makes it hard to know if your future care is actually covered.
- Confirm whether a Medicare Set-Aside (WCMSA) applies: if you are a Medicare beneficiary or have a reasonable expectation of enrolling within 30 months, CMS review may be appropriate.
- Understand the review threshold: CMS guidance on WCMSA review explains when CMS review and approval are appropriate and requires that an approved WCMSA be exhausted before Medicare pays for related care.
- Know the apportionment rules: under 42 CFR § 411.46, Medicare treats lump-sum compromise settlements as workers’ comp payments and sets rules for how allocated amounts affect Medicare’s payment responsibility.
- Get the allocation reviewed by an attorney or a qualified consultant before signing, especially if the offer is six figures or involves ongoing care.
A WCMSA must generally be exhausted before Medicare will pay for related treatment, per CMS guidance, which means an undervalued medical allocation can leave you paying out of pocket for years after settlement.
Ignoring Medicare’s interest is not a minor paperwork problem. It can expose both the claimant and the payer to future recovery claims, which is exactly why insurers build this check into larger hip settlements involving surgery or replacement.
What You Get If You Don’t Settle: TTD, PPD, and Ongoing Medical Coverage
Settling is not the only option. If you keep your claim open, you continue receiving benefits under the standard workers’ comp structure.
- Temporary Total Disability (TTD) pays a percentage of your average weekly wage while you are unable to work at all, typically until you reach MMI or return to some form of duty.
- Permanent Partial Disability (PPD) pays based on your impairment rating once your condition stabilizes, often as a scheduled award for a specific body part or as a percentage of total disability.
- Open medicals mean the insurer keeps paying for related treatment indefinitely, which can be worth more than a lump sum if you expect future surgery, while closed medicals cut off that coverage at settlement.
Insurers calculate lump-sum offers by discounting the present value of expected future payments, which usually means the lump sum is worth less than the sum of what you would receive if every future payment arrived on schedule. That tradeoff is worth weighing carefully, especially for a hip injury where revision surgery down the road is a real possibility.
Do You Need a Lawyer? When Legal Help Changes the Outcome
Attorney involvement tends to matter most in specific situations rather than every claim.
- Surgical cases, where permanent impairment ratings and future medical allocations carry real dollar weight.
- Disputed causation, where the employer or insurer argues your hip condition is unrelated to work or preexisting.
- Large future medical needs, where a hip replacement or anticipated revision surgery makes the medical allocation the biggest line item.
- WCMSA complexity, where Medicare set-aside rules require careful structuring to avoid future coverage gaps.
Most workers’ comp attorneys work on contingency, taking a percentage of the settlement rather than charging upfront, so confirm the fee percentage and what it covers in writing before signing a retainer. Bring your medical records, wage statements, and a calculator estimate to the first consultation so the attorney can give you a realistic read on your case rather than a guess.
State Filing Deadlines and Immediate Steps to Protect Your Claim
Deadlines for filing a workers’ compensation claim vary by state, commonly ranging from six months to two years, according to FindLaw’s state-by-state summary. Missing your state’s deadline can bar your claim entirely, so speed matters from day one.
- Report the injury to your employer immediately, in writing if possible, and keep a copy for your own records.
- Seek medical treatment and document everything, including the date, the provider, and how the injury happened.
- File the required state and employer forms within your jurisdiction’s deadline, which your state’s labor or workers’ comp agency can confirm.
- Preserve evidence, including photos of the hazard, witness names, and any incident reports filed at the time.
If you are approaching a deadline or unsure which forms apply, contact a workers’ comp attorney or your state labor office immediately rather than waiting. Readers filing in California can review a state-specific filing guide for practical steps on timelines and required documentation.
How to Produce a Realistic Estimate Before You Negotiate
A reliable estimate starts with the right inputs: your state, your average weekly wage, your date of injury, and whether surgery or a PPD rating is expected. Each of those changes the math significantly, because every state sets its own maximum weekly benefit cap.
- State matters more than people expect: a worker in Illinois and a worker in California with identical wages can receive different weekly benefits because each state caps TTD and PPD differently.
- Surgery and PPD assumptions shift the total: a calculator that lets you toggle surgical status gives a more realistic settlement range than a flat average.
- Save your results: a printed or saved estimate becomes a useful anchor point when a carrier’s first offer comes in low.
The Free Workers’ Comp Calculator models these state caps directly, and injury-specific tools like the shoulder injury calculator show how surgical cases change projected settlement ranges for other body parts facing similar dynamics.
Pro Tip: Bring your saved calculator estimate, your wage statements, and your medical records to any negotiation or attorney consult: having your own number makes it much harder for an adjuster to anchor low.
Common Disputes in Hip Workers’ Comp Claims and How to Handle Them
Three disputes come up repeatedly in hip injury claims. The first is causation: employers sometimes argue the hip condition stems from age-related arthritis or a prior injury rather than the workplace incident. Detailed medical records tying the injury to a specific work event are your best defense here.
The second is the permanent impairment rating itself. Insurers sometimes rely on a company doctor’s rating that undervalues your functional loss compared to what your own treating physician documents. Requesting a second opinion or an independent evaluation can close that gap.
The third is the medical allocation in a proposed settlement, particularly when future surgery or hardware replacement is likely. A vague allocation that does not account for a probable revision surgery down the road can leave you underfunded years later. In each case, the fix is the same: get the dispute in writing, gather supporting medical documentation, and do not sign anything that resolves the dispute against your favor without review from an attorney or qualified advocate.

The Role of Independent Medical Examinations in Settlement Decisions
An independent medical examination (IME) is an evaluation performed by a doctor chosen by the insurer, not your treating physician, and it often plays a decisive role in settlement value. Insurers use IMEs to challenge a treating doctor’s diagnosis, impairment rating, or recommendation for further treatment, particularly when a hip replacement or extensive surgery is on the table.
An IME that disagrees with your treating doctor does not automatically control the outcome, but it does give the insurer leverage to offer less or dispute ongoing treatment. If you are scheduled for an IME, bring your full medical history, be specific and consistent about your symptoms and limitations, and avoid minimizing your pain out of politeness. A conflicting IME finding is often the point where a second opinion or legal advocacy becomes worth pursuing, especially when the gap between the two assessments affects your permanent impairment rating.
How Vocational Rehabilitation and Return-to-Work Programs Affect Settlement Value
Vocational rehabilitation programs help injured workers who cannot return to their prior job find new employment, often through retraining, job placement assistance, or modified duty arrangements. Participation can cut both ways in settlement negotiations. On one hand, a successful return to work, even in a different role, can reduce the wage-loss component of your claim because it demonstrates ongoing earning capacity. On the other hand, if a hip injury genuinely prevents you from returning to physically demanding work, documented failed attempts at vocational rehabilitation can strengthen your case for a higher PPD award or extended wage-loss benefits.
Insurers sometimes push early return-to-work offers specifically to reduce a claim’s value, so it is worth evaluating whether a light-duty position is a genuine fit or a token role designed to cut off TTD payments. A vocational counselor’s written assessment of your transferable skills and physical restrictions carries real weight if the case ends up in negotiation or a hearing.
Negotiation Priorities and the Mistakes That Cost Workers the Most
If I had to rank priorities, future medical allocation comes first. A settlement that covers today’s bills but ignores tomorrow’s revision surgery is a settlement that fails you later. Confirming Medicare’s interest runs a close second, since skipping it creates headaches years down the road.
The costliest mistakes I see: signing before the allocation is itemized, ignoring WCMSA requirements entirely, and accepting a PPD rating without questioning whether it reflects your actual loss of earning capacity.
— Daniel
Get a Personalized Hip Settlement Estimate in Minutes
Every state sets a different weekly benefit cap, which means a national average only gets you so far. The Free Workers’ Comp Calculator builds in each state’s 2026 benefit caps so your TTD and PPD numbers reflect what your state actually pays, not a blended national figure.
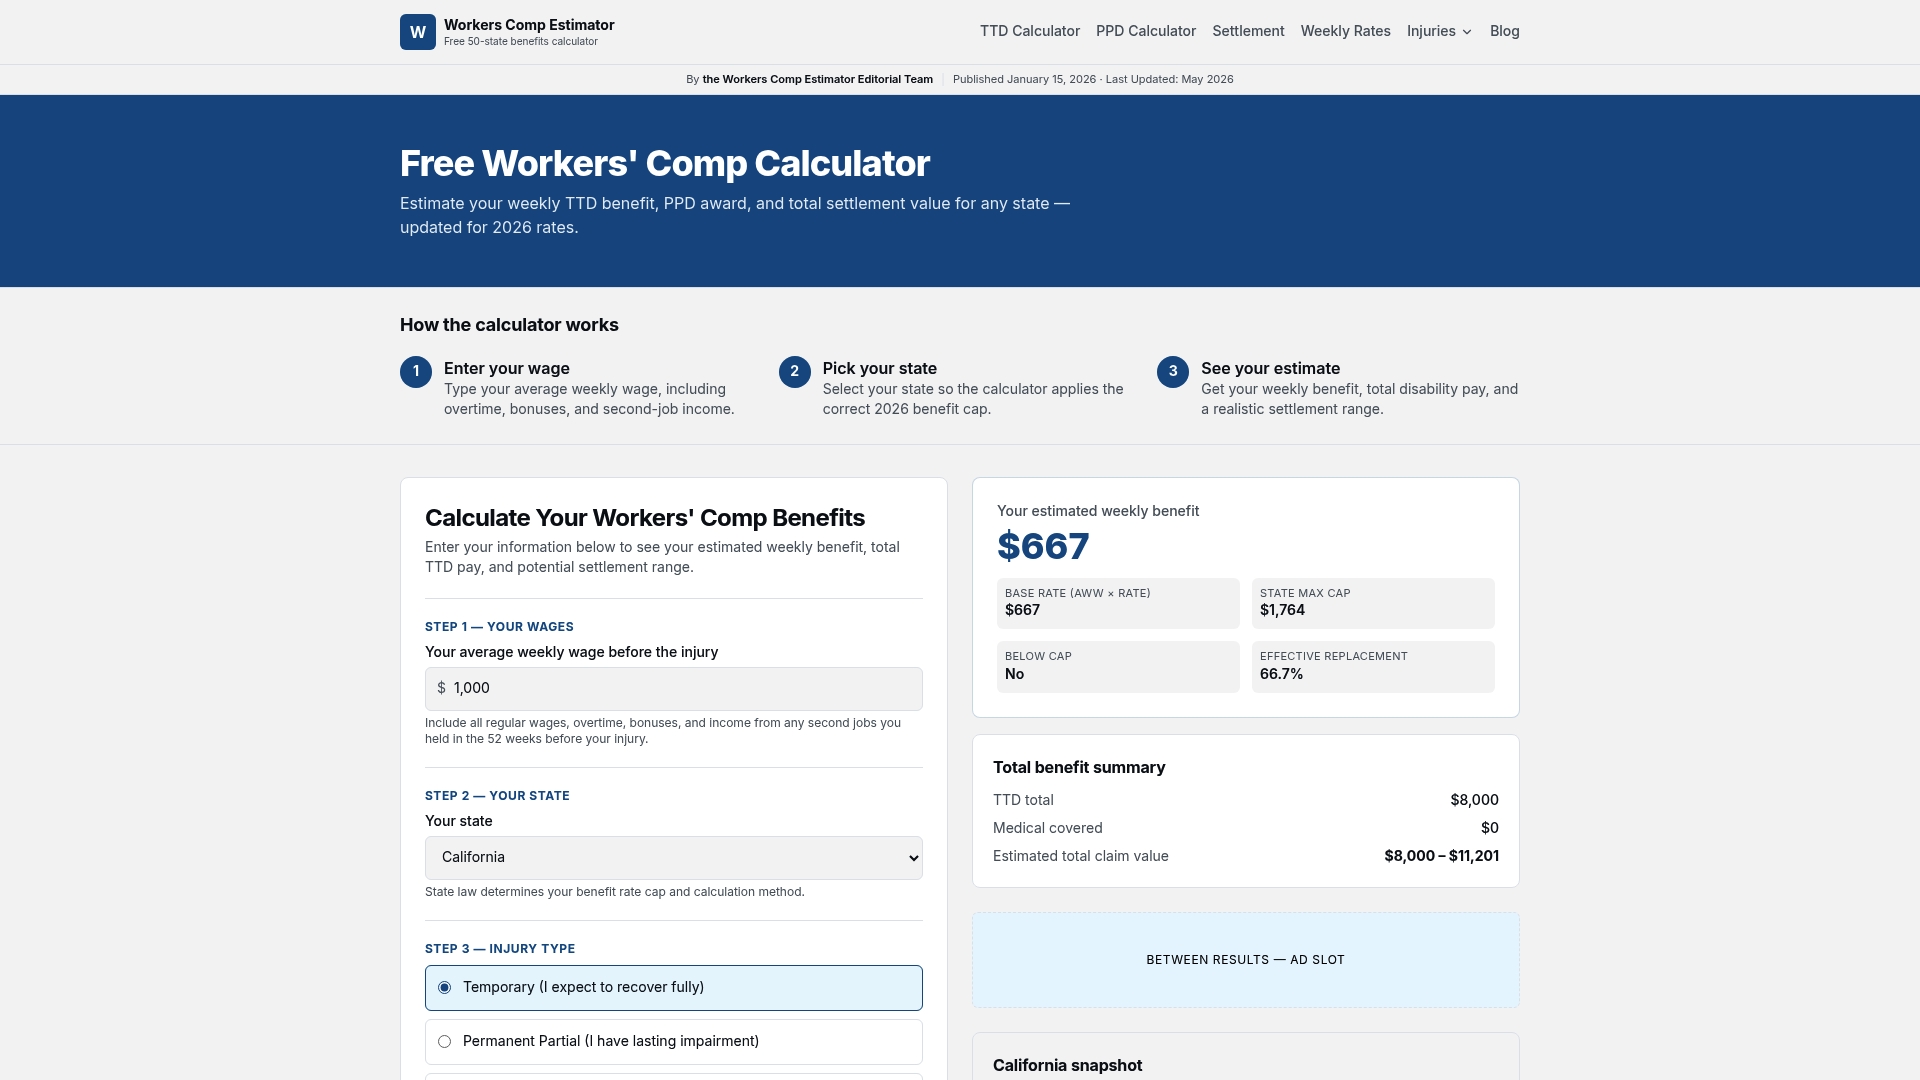
- Enter your state, average weekly wage, and injury details to see a personalized weekly benefit and settlement range.
- Review injury-specific tools, including the back injury calculator, to see how surgical and non-surgical outcomes differ.
- Save your estimate and bring it to a carrier negotiation or an attorney consultation as a starting anchor.
Run the numbers at Workerscompestimator before you respond to any settlement offer, so you know whether the number on the table reflects your actual case or just a generic average.
This article is general information, not a substitute for advice from a qualified financial advisor. Consult a qualified financial professional about your own circumstances before acting on anything here.
FAQ
How much does workers’ comp pay for hip replacement?
Payment depends on your state’s weekly benefit cap, your average weekly wage, and your permanent impairment rating after surgery. A state-specific calculator that models your wage and state cap gives a far more accurate figure than a national average.
What is the typical settlement amount for a hip injury?
Workers’ comp claims involving the hip, thigh, or pelvis averaged $66,634 in total claim costs for injuries occurring in 2022 and 2023, according to Injury Facts. Individual settlements vary widely based on whether surgery was required and how significant the permanent impairment rating is.
Is total hip replacement considered a permanent disability?
A hip replacement often results in a permanent partial disability rating because it typically leaves some lasting restriction on range of motion or physical activity. The exact rating depends on your specific recovery and is assigned by a treating or independent physician once you reach maximum medical improvement.
What is a fair settlement for workers’ comp?
A fair settlement fully covers your documented future medical needs, including any Medicare set-aside requirements, and fairly compensates lost wages and permanent impairment. Adjudicators weigh factors like age, work history, degree of disability, and future medical needs when judging settlement adequacy, according to SSA’s policy analysis.
When is a Medicare Set-Aside required in a hip settlement?
A WCMSA may be appropriate when you are a Medicare beneficiary or have a reasonable expectation of enrolling within 30 months, and CMS review applies above certain thresholds, per CMS guidance. A CMS-approved WCMSA generally must be exhausted before Medicare pays for related treatment.
Sources
- Workers’ Compensation Costs - Injury Facts
- WCMSA reference guide — CMS (version 4.6, July 13, 2026)
- 20 CFR § 702.243 - Settlement application; how submitted, how approved, how disapproved
- 42 CFR § 411.46 - Lump-sum payments
- Compensating Workers for Permanent Partial Disabilities (SSA Social Security Bulletin)
Recommended
More from the blog
Learn how MMI changes your workers' comp benefits, appeal deadlines, and settlement choices — and run the free 50‑state estimator to estimate your likely...
U.S. guide for Medicare eligible claimants: see the $25,000/$250,000 CMS review triggers, learn funding and admin options, and use free 50 state...
Compare workers comp and personal injury for U.S. workers. Learn which deadlines matter, how liens reduce settlements, and use the free 50 State...
Free workers' comp calculators
Put the numbers in this article to work on your own claim.
Weekly benefit, PPD, and settlement in one place.
What your weekly temporary disability check should be.
Scheduled weeks and permanent impairment awards.
Light-duty benefit when you earn less while healing.
Federal employee FECA award by body part.
Lump-sum value of your full claim.
Turn a 5%, 10%, or 20% rating into dollars.
Max and min weekly rates for all 50 states.
Typical settlement ranges by injury and state.
Average settlement for fusion, rotator cuff, knee replacement, and more.
Why comp does not pay it, and when a third-party claim does.
When carriers typically make an offer.
What coverage costs by class code and payroll.
Guides, state updates, and claim strategy.